

CRISPR off-target analysis is the process of predicting, detecting, and confirming unintended genome edits caused by a guide RNA and nuclease pairing. The reliable approach combines variant-aware in silico prediction with at least one unbiased experimental discovery method, then confirms candidate sites with targeted deep sequencing. Consult GUIDE-seq or CIRCLE-seq for discovery and DISCOVER-Seq+ when in vivo relevance matters.
TL;DR:
- Off-target effects can cause large deletions or chromosomal translocations, heavily influenced by chromatin accessibility and cell-specific DNA repair pathways.
- Computational tools like Cas-OFFinder and CRISPRitz are fast but generate many candidates; functional annotation and variant data are essential for prioritization.
- Cell-free assays are highly sensitive but often produce false positives, whereas in vivo methods like DISCOVER-Seq+ offer more accurate, tissue-relevant detection.
- Validation requires deep sequencing with controls, considering structural variants and setting detection limits explicitly to prevent misinterpretation.
- Using high-fidelity nucleases, optimized guide design, and delivery methods that limit nuclease exposure significantly reduce off-target risks before testing begins.
Table of Contents
- What CRISPR Off-Target Effects Are and Why They Matter
- In Silico Prediction: Algorithms, Scoring Systems, and Practical Tool Selection
- Experimental Detection Methods Compared: Cell-Free, Cell-Based, and In Vivo
- Analysis, Prioritization, and Validation: Turning Candidate Sites Into Reliable Calls
- Practical Strategies to Minimize Off-Target Editing
- Recommended Workflow: Stepwise Pipeline From Prediction to In Vivo Confirmation
- How Patient-Specific Modeling Sharpens Off-Target Validation
- Where the Field Still Falls Short
- How Hopeatrarelabs Supports Off-Target Validation Work
- Sources
- FAQ
What CRISPR Off-Target Effects Are and Why They Matter
An off-target effect happens when Cas9, or another CRISPR nuclease, cuts a genomic sequence that resembles the intended guide RNA target but isn't the actual site you designed for. The nuclease doesn't require a perfect match. It tolerates mismatches, particularly toward the 5' end of the guide, and it can still cut through DNA/RNA bulges where an extra base loops out of the hybrid. PAM sequence requirements add another layer of unpredictability. Cas9 typically needs an NGG PAM adjacent to the target, but partial recognition of degenerate PAM-like sequences elsewhere in the genome opens the door to unintended cleavage.
The guide RNA's own thermodynamics shape this risk. A guide with high binding stability at its 3' seed region will tolerate more mismatches elsewhere and still find and cut a near-match sequence. That's the mechanical half of the problem. The other half is what happens after the cut.
Repair outcomes at off-target sites vary widely, and each carries different downstream consequences:
- Small insertions or deletions (indels) at the cleavage site, usually a few base pairs
- Large deletions spanning kilobases, which can silence or truncate nearby genes
- Chromosomal translocations, especially when two simultaneous double-strand breaks occur on different chromosomes
- Unintended RNA or DNA base changes from base editors, which don't cut DNA but can still deaminate bases at unintended loci
None of these outcomes occur uniformly across cell types. Chromatin accessibility strongly influences whether a predicted site is ever actually cut. A sequence that looks like a strong off-target on paper may sit in closed heterochromatin in your target cell type and never get touched by the nuclease. The reverse also happens: open chromatin regions can produce cutting at sites your algorithm scored as low risk. The DNA repair pathway available in a given cell state (whether non-homologous end joining or homology-directed repair dominates) changes both the type and frequency of the resulting mutation.
This is why regulators and the PMC review on CRISPR/Cas9 off-target effects both push for orthogonal validation using multiple methods, and, wherever feasible, confirmation in vivo. A computational prediction alone tells you almost nothing about clinical risk. A cell-free biochemical assay tells you more, but still misses the biology. Only evidence gathered in the correct cellular or organismal context tells you what will actually happen to a patient.
In Silico Prediction: Algorithms, Scoring Systems, and Practical Tool Selection
Computational prediction is where every off-target workup should start, mostly because it's fast and cheap. It is also, by a wide margin, the least reliable stage in the pipeline. Treat every in silico hit as a hypothesis to test, not a fact.
Prediction tools split into two conceptual camps. Alignment-based approaches enumerate every genomic sequence within a defined number of mismatches (and often bulges) from your guide, then rank them by similarity. Scoring-based approaches go a step further and try to model the biochemistry, weighting mismatch position, PAM strength, and sometimes chromatin accessibility to estimate a probability of cleavage rather than just counting mismatches.
CFD (Cutting Frequency Determination), built on the Doench lab's rules, and the older MIT/Hsu score are the two scoring systems you'll see cited constantly. Both were trained on empirical cutting data from specific cell lines and guide sets, which is exactly where their limitations show up. A CFD score reflects patterns learned from the training data it was built on, not universal biochemistry. Guides with unusual mismatch patterns or novel PAM variants can get scored inaccurately simply because nothing like them appeared in the training set. The PMC mechanistic review of the CRISPR-Cas9 machinery notes that these limitations tied to training data remain a persistent issue even as scoring models get refined.
Here's how the three tools you'll actually use for daily work differ in practice:
- Cas-OFFinder performs exhaustive genome-wide search for sequences matching your guide within a specified mismatch and bulge tolerance. It doesn't score or rank; it enumerates. Use it when you want to be certain you haven't missed a candidate, and you're willing to filter the output yourself. The Cas-OFFinder tool has been a workhorse since its original Bioinformatics publication, and it remains the reference point most other tools benchmark against.
- CRISPRitz builds on the same exhaustive search logic but adds variant awareness, meaning it can incorporate population-level SNPs or a patient's own genomic variants into the search. This matters enormously for translational work: a guide that looks clean against the reference genome can pick up a new, higher-risk off-target if a patient carries a common SNP that recreates a near-match PAM.
- CRISPOR wraps prediction, CFD/MIT scoring, and functional annotation (functional annotations such as nearby genes, exonic overlap, and conservation) into a single interface. It's the fastest way to get a prioritized, annotated candidate list without stitching together three separate outputs yourself.
None of these tools tells you whether a candidate site will actually get cut in your cell type. They tell you which candidates deserve experimental attention first.
Pro Tip: Don't rely on a single score cutoff to eliminate candidates. A guide with a moderate CFD score but perfect sequence match within an exon of a tumor suppressor gene deserves more attention than a guide with a lower score sitting in an intergenic desert. Rank by a combination of sequence similarity, gene proximity, and expression in your target cell type, not raw score alone.
Practical prioritization comes down to a few heuristics that hold up across most projects. Filter first by PAM compatibility and total mismatch count, typically keeping anything within 3 to 4 mismatches or one bulge. Then re-rank by functional annotation, pushing candidates inside coding exons or regulatory elements to the top regardless of their raw score. Cross-reference against patient-specific or population variant databases if you're working toward a clinical application, since a reference-genome-only search will systematically miss variant-created off-targets. Finally, cap the list at a number you can realistically validate experimentally. A list of 500 unranked candidates is not a prioritization; it's a spreadsheet nobody will finish reviewing.
Experimental Detection Methods Compared: Cell-Free, Cell-Based, and In Vivo
In silico predictions overshoot reality by a wide margin. Analyses across method-comparison studies consistently show that many predicted off-target sites never validate in an actual cellular context, which is precisely why experimental detection sits at the center of any serious off-target crispr tests strategy. Three tiers of experimental methods exist, and each answers a different question.
Cell-free methods work directly on purified genomic DNA outside a cell. CIRCLE-seq circularizes genomic DNA fragments, then exposes them to the Cas9/guide RNA complex in a test tube; any circle that gets linearized by cleavage gets sequenced and mapped back to its genomic origin. SITE-seq follows a similar biochemical logic. Both methods are extremely sensitive because there's no chromatin, no competing cellular machinery, and no limit on nuclease exposure time. That sensitivity is also their weakness. Without chromatin to restrict access, these assays generate a large number of candidate sites that a real cell would never actually expose to the editing complex. Cell-free discovery data has low cellular validation rates precisely because it strips away the biology that determines real-world risk.
Unbiased cell-based methods solve that problem by working inside living cells. GUIDE-seq co-delivers a short double-stranded oligonucleotide tag that gets incorporated at any double-strand break site, including off-targets, and then sequences around every tagged location genome-wide. CHANGE-seq is a related, higher-throughput biochemical method that bridges some of the gap between cell-free and cell-based approaches. Both give you results shaped by actual chromatin accessibility and cellular repair activity, which produces a shorter, more biologically believable candidate list than cell-free discovery, generally at some cost to raw sensitivity.
In vivo-compatible methods answer the question regulators actually care about: what happens in the target tissue itself. DISCOVER-Seq tracks the recruitment of DNA repair proteins like MRE11 to double-strand break sites using chromatin immunoprecipitation, essentially watching the cell's own repair machinery point to where cuts happened. DISCOVER-Seq+ improves on this by pairing MRE11 ChIP-seq with DNA-PKcs inhibition, which extends how long repair proteins linger at break sites and makes them easier to capture.
Sensitivity gain: DISCOVER-Seq+ increased off-target discovery sensitivity by notably increased across various cell lines, primary human cells, and mouse models compared with earlier in vivo detection methods. That's a meaningful jump for any program trying to characterize risk in a tissue that can't easily be biopsied or cultured at scale.
Once discovery narrows a candidate list, targeted verification methods take over. Amplicon deep sequencing (targeted NGS at specific loci) can catch indel frequencies well below 1%, provided you sequence deep enough and run proper unedited controls. UDiTaS goes further by capturing structural rearrangements, including translocations and large deletions, that standard amplicon sequencing simply can't see because it assumes the amplified region stays structurally intact.
A quick comparison of where each tier fits:
| Method Tier | Sensitivity / Discovery Breadth | False Positive / Validation Risk | Applicability | Throughput and Cost | Best Suited For |
|---|---|---|---|---|---|
| Cell-free (CIRCLE-seq, SITE-seq) | Highest raw sensitivity | High false positive rate; low cellular validation | In vitro only | Moderate cost, high throughput | Exploratory candidate generation |
| Unbiased cell-based (GUIDE-seq, CHANGE-seq) | Moderate to good | Lower false positive rate than cell-free | Cell lines, primary cells | Moderate cost | Translational discovery |
| In vivo (DISCOVER-Seq, DISCOVER-Seq+) | Improved by up to fivefold with DISCOVER-Seq+ | Most biologically representative | In vivo tissues, animal models | Higher cost, lower throughput | Clinical/preclinical validation |
| Targeted verification (amplicon NGS, UDiTaS) | Detects sub-1% indel frequencies and structural variants | Very low false positive rate when properly controlled | Any candidate locus | Low cost per site, scalable | Final confirmation before decision-making |
No single tier substitutes for another. Cell-free discovery casts the widest net; in vivo methods tell you what's clinically real; targeted verification closes the loop with statistical confidence at each specific locus.
Analysis, Prioritization, and Validation: Turning Candidate Sites Into Reliable Calls
A raw list of candidate off-target sites is not an answer. It's a queue. The job of analysis is deciding which candidates get scarce experimental time and which get set aside, and doing that consistently enough that another lab could reproduce your reasoning.
Prioritization should weigh several factors together, never any single one in isolation:
- Sequence similarity to the intended target, weighted by mismatch position rather than raw count, since a mismatch near the PAM matters more than one at the guide's 5' end.
- Functional annotation, pushing candidates within coding exons, splice sites, or known regulatory elements above intergenic hits regardless of similarity score.
- Expression status in the actual target cell type, since a candidate site inside a gene that's silent in your cell context carries lower functional risk than one inside an actively expressed gene.
- Patient-specific or population variant overlap, because a candidate created or worsened by a common SNP changes the risk calculation for any therapeutic application.
Once a shortlist exists, validation sequencing needs enough depth to mean something. Detecting low indel frequencies in the sub-percent range, where many clinically relevant off-target events occur, requires substantially higher read depth than a typical exome run, along with matched unedited controls sequenced at the same depth to establish background error rate. Running biological replicates, not just technical replicates of the same sample, catches variability introduced by delivery efficiency or cell state that a single replicate will miss entirely.
Orthogonal confirmation matters just as much as depth. A site flagged by one discovery method and independently confirmed by targeted sequencing carries far more weight than a site that only ever showed up once. When a candidate site involves potential structural rearrangement rather than a simple indel, standard amplicon sequencing won't catch it. That's when structural-variant-aware assays like UDiTaS or LAM-HTGTS earn their place in the workflow, since both are built to detect translocations and large deletions that amplicon approaches structurally cannot see.
Pro Tip: Document your limit of detection explicitly for every validation assay, and set a decision rule before you look at the data, not after. If your amplicon sequencing depth gives you a limit of detection around 0.1%, state that number in your report and treat anything below it as "not detected at current sensitivity," not "absent." That single habit prevents a huge amount of downstream misinterpretation.
The output of this stage should be a documented decision, not a data dump: which sites are confirmed, which are ruled out with a stated confidence level, and which remain ambiguous enough to warrant functional testing before any conclusion gets drawn.
Practical Strategies to Minimize Off-Target Editing
The best off-target analysis in the world doesn't help much if the underlying guide design was sloppy. Reducing off-target risk starts well before any sequencing run, at the design table.
Guide RNA selection is the first and highest-leverage lever. Score-guided selection using CFD or MIT/Hsu scores should rule out guides with unusually high genome-wide mismatch tolerance (sometimes called high GMT guides), even when they score well on-target efficiency. Bulge-tolerant near-matches deserve careful scrutiny as well, given that guides appearing clean under no-bulge searches can have problematic bulge-tolerant off-targets elsewhere in the genome. And any design pipeline aimed at clinical or translational work should screen against common population SNPs, not just the reference genome, since a guide scoring cleanly against reference sequence can still create a new off-target in patients carrying frequent variants.
Nuclease choice is the second lever, and it has gotten considerably more nuanced in recent years:
- High-fidelity Cas9 variants (engineered to reduce non-specific DNA contacts) cut on-target activity somewhat but reduce off-target tolerance substantially, making them worth the trade-off for most clinical applications.
- Nickases, which cut only one DNA strand, require paired guides for a functional double-strand break, and this pairing requirement inherently reduces off-target risk since both guides would need to match at a nearby off-target site simultaneously.
- Base editors and prime editors avoid double-strand breaks entirely for many edit types, which changes the off-target risk profile away from indels and translocations and toward unintended base conversions, still requiring dedicated off-target analysis, just of a different kind.
Delivery and dosing form the third lever, and it's often underused relative to how much control it offers. Delivering Cas9 as a ribonucleoprotein complex rather than as a plasmid or viral vector limits the nuclease's presence in the cell to a short window, typically clearing within 24 to 48 hours, which directly reduces the time available for off-target cutting to occur. Titrating dose downward toward the minimum effective concentration reduces off-target activity even when it costs some on-target efficiency, and timed or inducible delivery systems can further limit total nuclease exposure in sensitive applications.
Chemical modifications to the guide RNA itself, along with continued enzyme engineering, round out the toolkit. Modified guides with altered backbone chemistry can reduce off-target binding stability without sacrificing on-target activity, and newer engineered nuclease variants continue to push the specificity ceiling higher than earlier Cas9 versions could reach.
Recommended Workflow: Stepwise Pipeline From Prediction to In Vivo Confirmation
Every reliable off-target analysis pipeline follows roughly the same shape, even when the specific tools change. Here's the sequence that holds up across most projects, whether you're running exploratory research or preparing a preclinical safety package.
- Run variant-aware in silico enumeration. Use Cas-OFFinder or CRISPRitz to exhaustively search for candidate sites, incorporating patient-specific or population variants when the application is clinical. Filter the raw output by functional annotation, keeping candidates in coding regions or regulatory elements regardless of raw mismatch score.
- Choose a discovery method matched to your project's stage. Cell-free methods like CIRCLE-seq are appropriate for early, exploratory candidate generation where casting the widest net matters more than precision. For clinically relevant contexts, move to cell-based discovery with GUIDE-seq or, when in vivo relevance is essential, DISCOVER-Seq+.
- Verify with targeted deep sequencing and structural-variant assays. Amplicon NGS confirms indel frequencies at specific loci; add UDiTaS when a candidate site raises concern for structural rearrangement rather than a simple indel.
- Confirm in biologically relevant cells, and escalate to in vivo when the application demands it. Primary cells or iPSC-derived cells matching the intended target tissue give you a far more meaningful readout than an immortalized cell line. When a therapeutic program is heading toward the clinic, in vivo confirmation in an animal model becomes the standard the PMC review points to for genuinely clinical-grade evidence.
A few practical notes on timing and stopping points:
- Budget roughly one to two weeks for in silico enumeration and filtering on a typical single-guide project.
- Cell-based discovery assays like GUIDE-seq generally take three to six weeks from delivery to sequenced results, depending on cell type and read depth.
- Stop escalating to more expensive methods once a candidate list stabilizes across two independent discovery methods and targeted sequencing confirms the expected sites within your predefined limit of detection.
- If your unedited controls and your edited samples show statistically indistinguishable rates at a candidate site, that's a legitimate stopping point, not a reason to keep testing.
How Patient-Specific Modeling Sharpens Off-Target Validation
Off-target validation means something different once you're working with a specific patient's cells rather than a generic cell line. A candidate site that looks silent in HEK293 cells might sit inside an actively transcribed gene in a patient's own fibroblasts or neurons, and that difference changes the entire risk calculation. Patient-specific disease models built from induced pluripotent stem cells (iPSCs) help researchers determine whether a predicted off-target actually matters for that patient by considering functional context, not just sequence context.
iPSC-derived target cells let researchers test candidate off-target sites in the correct cellular background, whether that's a specific neuronal subtype, a cardiomyocyte, or another tissue relevant to a given rare disease. This matters most when a CRISPR-edited isogenic control is being generated to compare against a patient's disease-causing variant. Any off-target edit introduced during that correction process could confound the comparison, so validating cleanly in the same cell type used for downstream drug or ASO screening isn't optional.
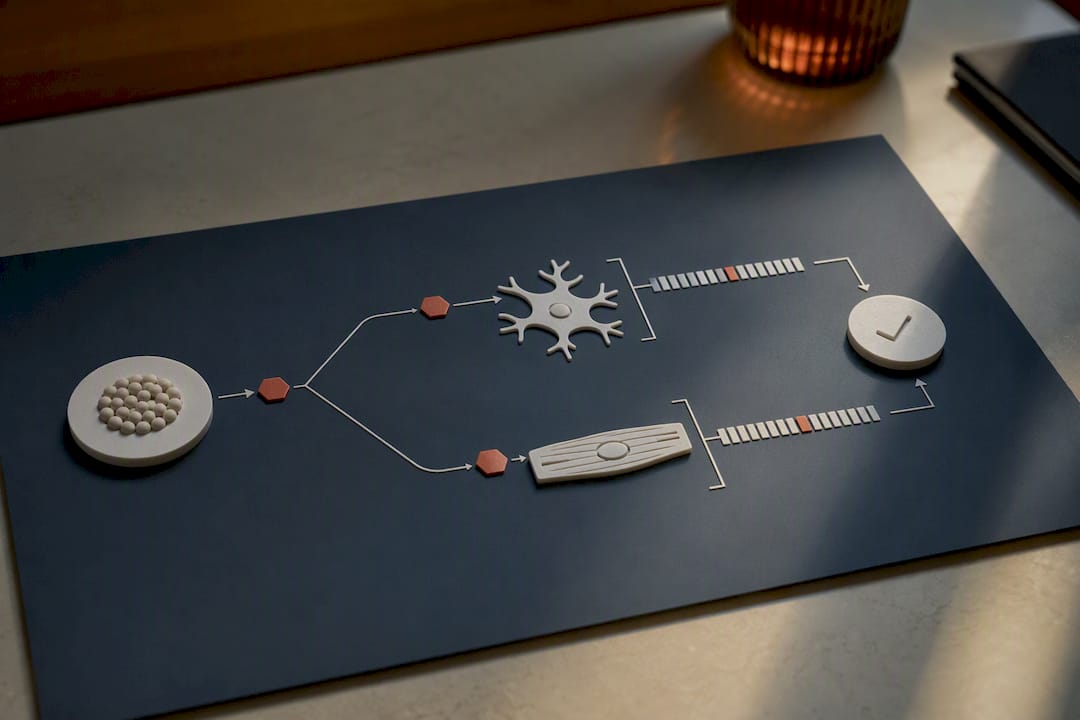
Parallel screening work, testing thousands of FDA-approved drugs alongside custom antisense oligonucleotides, depends on that same rigor. An unvalidated off-target hit hiding in the background of a screen can produce a false signal that looks like a therapeutic effect but is actually an editing artifact. Rigorous off-target assessment upfront is what keeps a screening result trustworthy downstream.
For readers working through related CRISPR workflow questions, Hopeatrarelabs covers iPSC-based allele correction workflows and ASO off-target assessment methods in more detail elsewhere on the site.
Where the Field Still Falls Short
The biggest gap in off-target analysis isn't sensitivity. It's standardization. Two labs can run reasonable, defensible pipelines on the same guide RNA and reach different confidence levels about the same candidate site, simply because neither followed a shared reporting standard. A recent commentary on this problem argues that inconsistent validation guidelines are actively slowing clinical translation, and having read through how differently even strong papers report limits of detection, I don't think that's an overstatement.
Multi-method pipelines aren't a nice-to-have layered on top of a "real" single test. They're the only honest way to characterize risk, since every individual method has a documented blind spot. The direction worth watching is higher-sensitivity in vivo detection paired with variant-aware risk scoring that accounts for a specific patient's genome rather than a generic reference. That combination is where off-target analysis stops being an academic exercise and starts actually protecting patients.
— John
How Hopeatrarelabs Supports Off-Target Validation Work
Fee-for-service research programs include patient-derived iPSC modeling, CRISPR editing workflows, and parallel drug and ASO screening for families, foundations, physicians, and biopharma partners tackling ultra-rare and undiagnosed genetic disease. If your off-target validation work needs a functionally accurate cellular model instead of a generic cell line, that's the specific gap this fills: testing candidate sites and therapeutic hits in cells that actually carry the patient's genetic background, not a proxy that might miss context-dependent risk entirely.
A first contact typically starts with a conversation about the specific disease, the patient's genetic profile, and what treatment options have already been ruled out or are worth screening in parallel. From there, Hopeatrarelabs scopes a program around iPSC modeling, editing, and screening tailored to that case. Every program is contracted individually as a fee-for-service research engagement, not a standardized product. If you're weighing whether patient-specific modeling makes sense for a program you're planning, visit the Hopeatrarelabs landing page to start that conversation.
Sources
Useful sources to consult when building or auditing an off-target pipeline:
- Improving the sensitivity of in vivo CRISPR off-target detection with DISCOVER-Seq+ | Nature Methods
- Off-target effects in CRISPR/Cas9 gene editing (PMC review)
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
FAQ
What Is an Off-Target Score in CRISPR?
An off-target score, such as CFD or MIT/Hsu, is a computational estimate of how likely a guide RNA is to cut a near-match genomic sequence rather than its intended target, based on mismatch position and count.
What Are the Off-Target Effects of CRISPR?
Off-target effects range from small insertions or deletions at unintended sites to large deletions, chromosomal translocations, and unintended base changes from base editors, with severity depending on cell type and repair pathway.
How Do Researchers Detect CRISPR Off-Targets?
Researchers combine in silico prediction tools like Cas-OFFinder or CRISPOR with unbiased experimental discovery methods such as GUIDE-seq, CIRCLE-seq, or DISCOVER-Seq+, then confirm candidates with targeted deep sequencing.
Why Does Cellular Context Matter for Off-Target Analysis?
Chromatin accessibility and cell-type-specific gene expression determine whether a predicted off-target site actually gets cut, which is why validation in patient-relevant cells, including iPSC-derived models, produces more reliable results than a generic cell line.
Which Method Gives the Most Clinically Relevant Off-Target Data?
In vivo-compatible methods like DISCOVER-Seq+ generally produce the most clinically relevant data, having shown up to a fivefold increase in detection sensitivity across cell lines, primary cells, and mouse models compared with earlier approaches.